Sideroblastic anemia
Sideroblastic anemia
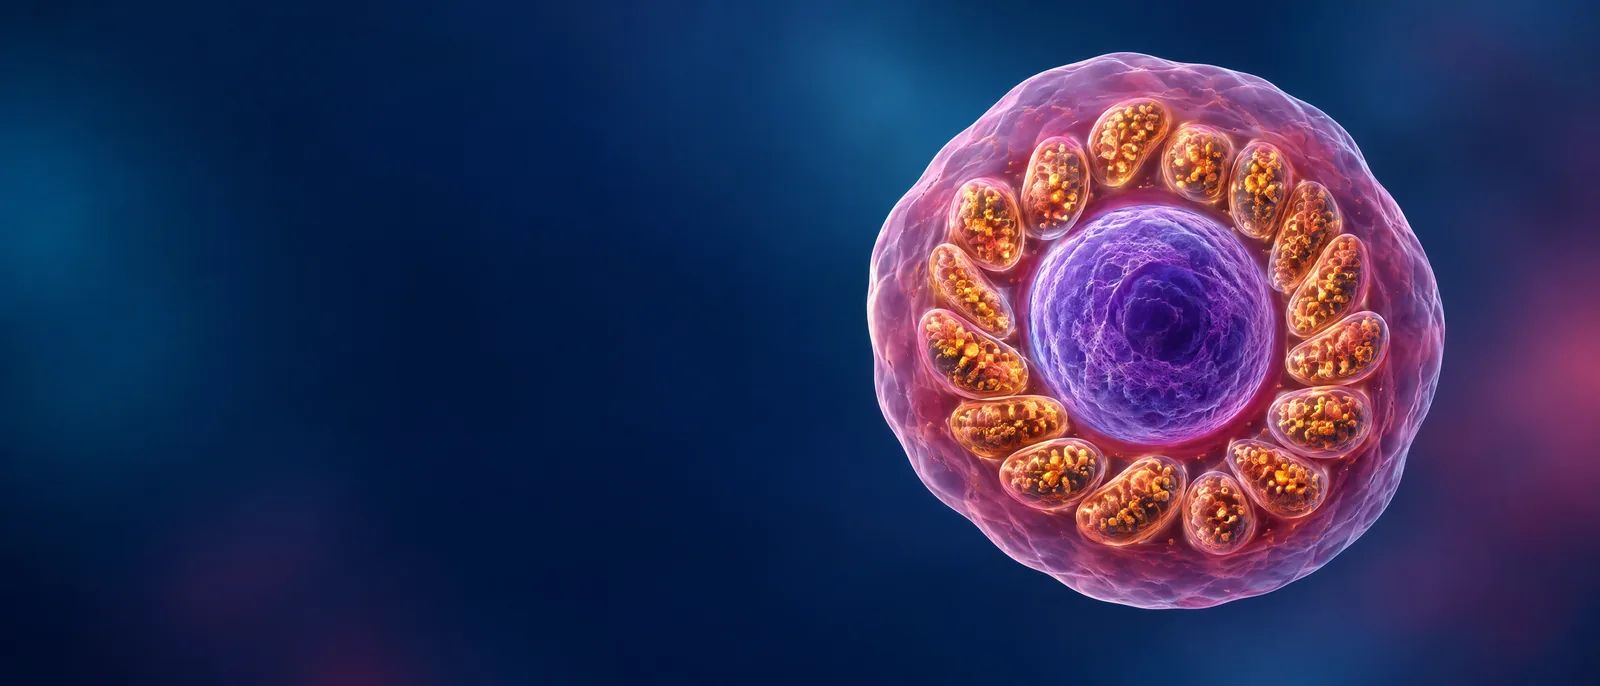
Pathophysiology

- Inherited and acquired bone marrow disorders of mitochondrial dysfunction, from defects in heme biosynthesis, iron-sulfur cluster biogenesis, generalized mitochondrial protein synthesis, or oxidative phosphorylation.
- Pathologic iron accumulation in the mitochondria of erythroid precursors. The iron-laden mitochondria encircle the nucleus, producing ringed sideroblasts on Prussian blue stain.
- Mechanistically, ringed sideroblasts form when there is either insufficient protoporphyrin production to use the iron delivered to erythroblasts, or defects in mitochondrial function that impair incorporation of iron into protoporphyrin.
- Iron studies resemble iron overload, not deficiency: this is an anemia with a defect of iron utilization, so iron studies are ELEVATED despite the anemia.
Causes
- Hereditary/congenital (generally microcytic; Pearson syndrome and TRMA are macrocytic):
- X-linked sideroblastic anemia (XLSA): missense mutation in ALAS2 (erythroid 5-aminolevulinate synthase); the most common hereditary form. Men typically present in the first 2 decades with microcytic anemia; carrier women can present in mid-to-late adulthood with normocytic or macrocytic anemia. Often pyridoxine (B6)-responsive. Iron overload develops over time.
- SLC25A38: most common form of autosomal recessive congenital sideroblastic anemia (non-syndromic).
- Mitochondrial DNA deletions: Pearson marrow-pancreas syndrome (sideroblastic anemia plus marrow precursor vacuolization plus exocrine pancreatic insufficiency plus lactic acidosis, in infants/children).
- SLC19A2: thiamine-responsive megaloblastic anemia syndrome (TRMA / Rogers syndrome): sideroblastic anemia plus diabetes mellitus plus sensorineural deafness.
- Acquired clonal (MDS-RS, generally macrocytic): SF3B1 mutation in >80%, which defines the WHO 2022 entity "MDS with low blasts and SF3B1 mutation" (favorable prognosis). Luspatercept-responsive.
- Drug-induced: isoniazid, cycloserine (anti-TB pyridoxine antagonists; co-administer B6), pyrazinamide (rare; mechanism unclear, stop drug); linezolid (inhibits mitochondrial protein synthesis); chloramphenicol.
- Alcohol: common acquired cause; reversible with abstinence.
- Lead poisoning: inhibits ALAD and ferrochelatase; basophilic stippling is classic.
- Copper deficiency (gastric bypass, malabsorption, parenteral nutrition without copper, chronic high-dose zinc) and zinc-induced copper deficiency (excess zinc supplementation, denture cream).
- Pyridoxine (B6) deficiency.
Congenital vs acquired: quick contrast
Sideroblastic anemia: congenital vs acquired
| Feature | Congenital/hereditary | Acquired |
|---|---|---|
| Typical MCV | Microcytic (Pearson syndrome and TRMA macrocytic) | Macrocytic (or normocytic); lead and B6 deficiency often microcytic |
| Prototype | XLSA (ALAS2); SLC25A38 (AR) | MDS-RS (SF3B1); alcohol, drugs, lead, copper deficiency |
| B6 responsiveness | Often (especially ALAS2) | Usually not (treat the cause) |
Diagnosis

- Iron studies: ↑ ferritin, ↑ transferrin saturation, normal TIBC (an iron-utilization defect, so iron studies are HIGH despite anemia).
- Smear: dimorphic population (microcytic plus normocytic); Pappenheimer bodies; coarse basophilic stippling (especially in lead poisoning).
- Bone marrow with Prussian blue: ringed sideroblasts (≥5 iron-laden mitochondria around at least one-third of the nuclear circumference).
- Lead level if exposure suspected.
- Genetic testing: ALAS2 (X-linked); SF3B1 in MDS-RS.
Treatment
- Pyridoxine (vitamin B6): for hereditary X-linked (ALAS2); many have a partial response.
- Remove the cause: stop the offending drug, treat lead poisoning, correct copper deficiency, abstain from alcohol.
- MDS-RS: luspatercept (FDA Apr 2020 after ESA failure; first-line ESA-naive lower-risk MDS Aug 2023 per COMMANDS), a TGF-β superfamily ligand trap, achieves transfusion independence in many. (See MDS section in malignant heme.)
- Allogeneic HSCT for severe hereditary or refractory disease.
- Monitor for and manage iron overload in chronic/transfusion-dependent disease.
High yield
- Ringed sideroblasts on bone marrow Prussian blue are diagnostic.
- Sideroblastic anemia looks like iron deficiency clinically but has ELEVATED iron studies.
- XLSA (ALAS2) is the most common hereditary form; try pyridoxine. SLC25A38 is the most common autosomal recessive congenital form.
- Congenital forms are usually microcytic (Pearson syndrome and TRMA are macrocytic); acquired forms are usually macrocytic (MDS-RS, alcohol), but lead poisoning and B6 deficiency are typically microcytic.
- SF3B1 mutation in MDS-RS: better prognosis; luspatercept-responsive.
- Lead poisoning: basophilic stippling plus microcytic anemia plus abdominal pain plus neuro/cognitive symptoms; check lead level.
- Linezolid, isoniazid, chloramphenicol, cycloserine, alcohol, copper deficiency: acquired drug/toxin/nutritional causes.
Veli Bakalov MD, Board Review Notes 2026