Chronic myeloid leukemia (CML)
Chronic Myeloid Leukemia (CML)
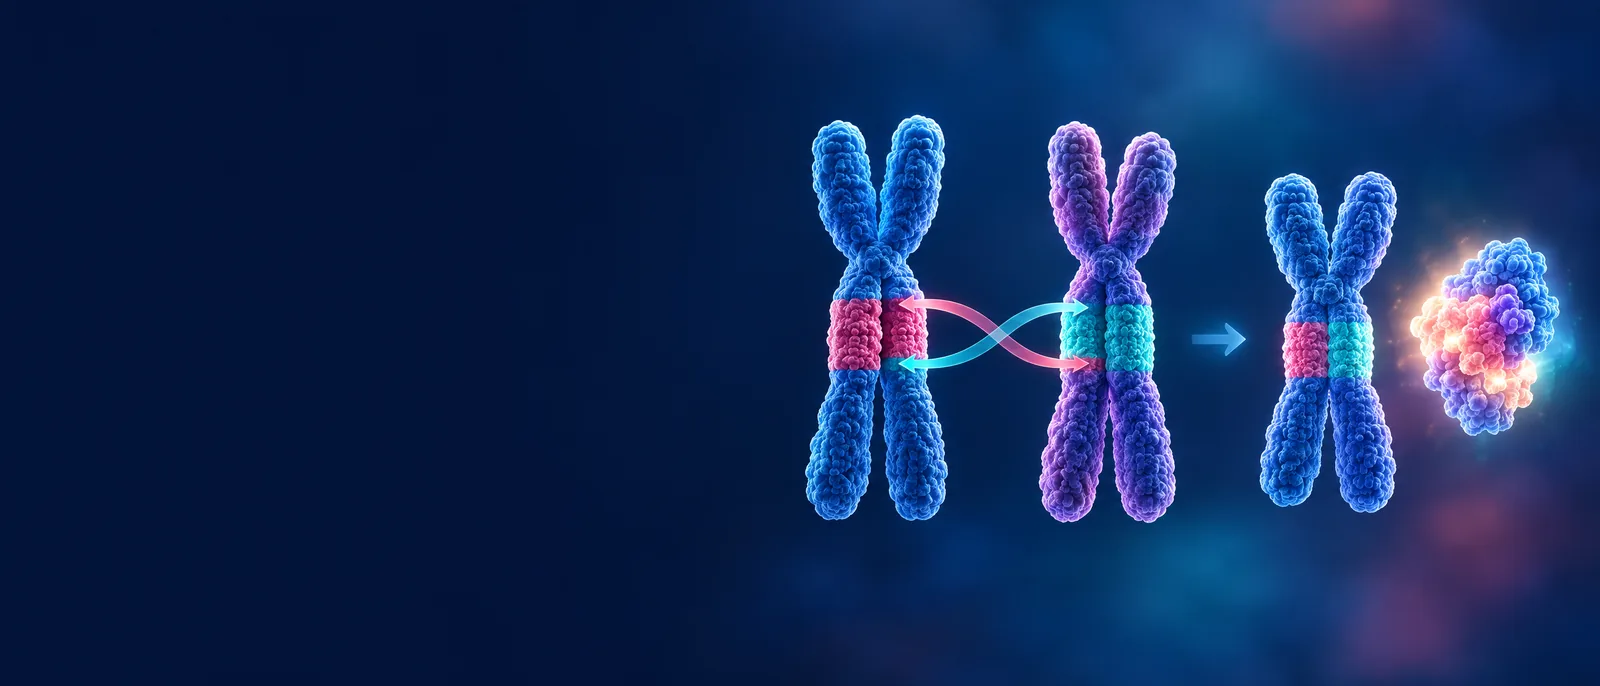
Pathogenesis

- Hallmark: myeloproliferative neoplasm of uncontrolled proliferation of mature and maturing granulocytes, defined by the Philadelphia chromosome, t(9;22)(q34;q11), which fuses BCR to ABL1. ABL1 tyrosine kinase catalytic activity becomes unregulated by fusion with BCR, driving uncontrolled granulocytic proliferation.
- Transcript variants: p210 (e13a2/e14a2, typical CML, including lymphoid blast crisis); p190 (e1a2, most Ph+ ALL with a different breakpoint, rare CML); p230 (e19a2, associated with chronic neutrophilia). ~98% express e13a2/e14a2; atypical transcripts (e1a2, e19a2, e13a3, e14a3) total ~1 to 2%, of which e13a3/e14a3 are a rare subset. CSF3R mutation is seen in chronic neutrophilia (CNL), not CML.
- Diagnosis of Ph: karyotype, FISH, or PCR for the p210 transcript. FISH is the first diagnostic test to send. BM aspirate + biopsy is mandatory for cytogenetics and phase determination.
- Ph-negative CML: ~5% lack the Ph chromosome despite the BCR-ABL1 rearrangement (cryptic insertion, or sequential translocations reconstituting normal chromosome morphology). If a presumed-CML patient is Ph-negative, evaluate for BCR-ABL1 expression: these patients may respond to TKIs.
- Epidemiology: median age ~65, ~9,000/yr US, ~15% of all leukemias. TKIs made CML a chronic disease with life expectancy approaching normal, so prevalence is rising.
Presentation & Diagnosis
- Symptoms: often asymptomatic (incidental WBC); fatigue, weight loss, night sweats, abdominal fullness from splenomegaly.
- Blood smear: leukocytosis with the full spectrum of the neutrophilic series, predominance of neutrophils and myelocytes ("myelocyte bulge"), basophilia and eosinophilia, thrombocytosis; NO dysplasia. LAP score is LOW (vs reactive leukocytosis, which has high LAP).
- Bone marrow: hypercellular, granulocytic hyperplasia, elevated M:E ratio, small hypolobated ("dwarf") megakaryocytes; reticulin may be present.
- Pre-treatment evaluation: BCR::ABL1 transcript on the International Scale (IS); kinase-domain (KD) mutation screen if AP/BP or TKI failure.
CML phases
CML phases
| Phase | Definition |
|---|---|
| Chronic phase (CP) | ~85% of patients at diagnosis; ~1% progress annually on TKI therapy (untreated CP historically progressed to BP in a median of 3 to 5 years). |
| Accelerated phase (AP) |
|
| Blast phase (BP) |
|
- WHO 2022 reclassified CML as a biphasic disease, eliminating AP as a distinct entity (high-risk features are now "CP with high-risk features" or BP); ICC 2022 retains AP; ELN 2025 acknowledges the controversy and does not fully endorse either classification.
- "Major route" additional cytogenetic abnormalities (ACAs): second Ph chromosome, trisomy 8, trisomy 19, isochromosome 17q (loss of 17p/TP53). Minor route = all others. Major-route ACAs associate with longer time to CCyR, lower MMR, shorter PFS and OS.
- Poor-prognosis baseline cytogenetics: i(17)(q10), -7/del(7q), 3q26.2 rearrangements.
Risk scoring at diagnosis
CML risk scoresSokal, Hasford, EUTOS, ELTS
| Score | Variables | Note |
|---|---|---|
| Sokal | Age, spleen, platelets, blasts | Original score; predicts response to imatinib. |
| Hasford (Euro) | Age, spleen, platelets, blasts + basophils + eosinophils | Adds basophils and eosinophils. |
| EUTOS | Basophils, spleen | Predicts response to imatinib. |
| ELTS | Age, spleen, platelets, blasts | Preferred in the TKI era; similar to Sokal for low-risk but better in high-risk patients. |
ELTS = EUTOS Long-Term Survival.
- Use: high-risk Sokal/ELTS favors a second-generation TKI or asciminib first-line; low-risk makes imatinib reasonable. Older age favors imatinib.
Response definitions

CML response definitionsHematologic, cytogenetic, molecular
| Level | Response | Definition |
|---|---|---|
| Hematologic | CHR | Complete hematologic response: Normal differential, WBC <10, platelets <450, no palpable splenomegaly, no circulating immature cells, <5% basophils. |
| Cytogenetic | MCyR | Major cytogenetic response: 0 to 35% Ph+ marrow metaphases. |
| CCyR | Complete cytogenetic response: 0% Ph+ marrow metaphases; target by 12 months. | |
| Molecular | MMR (MR3) | BCR-ABL1/ABL ≤0.1% IS; target by 12 months (ELN optimal). |
| MR4 | BCR-ABL1 ≤0.01% IS. | |
| MR4.5 | BCR-ABL1 ≤0.0032% IS (4.5-log reduction). | |
| MR5 | BCR-ABL1 ≤0.001% IS. |
- Milestones (ELN): 3 months optimal ≤10%; 6 months optimal ≤1%; 12 months optimal ≤0.1% (MMR); warning and failure thresholds escalate accordingly. Early molecular response (EMR, ≤10% by 3 to 6 months) is associated with good outcomes.
- Key concept: losing CCyR represents more substantial resistance than isolated loss of MMR, but mutation status cannot be inferred from either event; send kinase-domain mutation testing when resistance is suspected. CCyR at 12 mo and PCyR at 3 mo correlate with survival; MMR correlates with EFS. BM biopsy/cytogenetics at diagnosis; thereafter monitor response by peripheral-blood BCR::ABL1 qPCR (IS), repeating marrow only for failure to reach milestones, suspected progression, or unexplained cytopenias.
- ELN 2025 nuance: switching on failure is no longer automatic; individualize for comorbidity, transcript dynamics, prior toxicity. Prefer dose reduction to manage AEs over switching when efficacy is preserved. On failure, send BCR::ABL1 KD mutation analysis and check adherence and drug interactions first.
- Per NCCN, a patient with >50% reduction from baseline or a value minimally above the 10% cutoff can continue the same dose of dasatinib/nilotinib/bosutinib for another 3 months; imatinib should NOT be continued at the same 400 mg dose in that scenario (rationale for dose escalation).
TKI Therapy: first-line CP CML
CML First-line TKIs (FDA-approved options + dosing)
- Imatinib (Gleevec, 2001): 400 mg PO QD with food. First-gen ATP-competitive. Cheap (generic). Suitable for low-risk Sokal/ELTS. AEs: edema, GI upset, myelosuppression, muscle cramps, rash. IRIS 10-yr OS ~83.3% (68.6% high Sokal, 89.9% low Sokal; Hochhaus NEJM 2017). IRIS (O'Brien NEJM 2003): imatinib vs IFN-alfa + cytarabine; MCyR 87.1% vs 34.7%, CCyR 76.2% vs 14.5%, freedom from progression 96.7% vs 91.5%.
- Dasatinib (Sprycel, 2010 first-line): 100 mg PO QD CP, 140 mg AP/BP. Second-gen, broad-spectrum (also SRC), binds active and inactive ABL conformations. Crosses the BBB (best TKI option for CNS disease). DASISION (Kantarjian NEJM 2010): faster/deeper responses vs imatinib (12-mo confirmed CCyR 77% vs 66% (CCyR on any assessment 83% vs 72%); 5-yr cumulative MMR 76% vs 64%) but no OS/PFS difference at 5 yr (5-yr OS 91% vs 90%). AEs: pleural effusion (~20 to 28% over time; more common age >65), pulmonary HTN (rare, reversible), myelosuppression, bleeding (platelet dysfunction), QTc.
- Nilotinib (Tasigna, 2010 first-line): 300 mg PO BID newly dx, 400 mg PO BID second line. Empty stomach (no food 2 hr before / 1 hr after: bioavailability + QTc). ENESTnd (Saglio NEJM 2010): deeper MMR/MR4.5 vs imatinib (10-yr MMR ~78% vs 62.5%; 10-yr MR4.5 61% vs 39.2%) with no OS difference; 10-yr cumulative cardiovascular events 16.5 to 23.5% (nilotinib) vs 3.6% (imatinib). AEs: cardiovascular events (PAOD, MI, CVA; warning, not boxed), QTc prolongation (black-box; hold if QTc >480), hyperglycemia, hypercholesterolemia, hyperbilirubinemia (Gilbert/UGT1A1), pancreatitis. Nilotinib is dosed BID; asciminib is also BID in some regimens (40 mg BID option, 200 mg BID for T315I).
- Bosutinib (Bosulif, 2017 first-line): 400 mg PO QD newly dx, 500 mg QD second-line and beyond. Dual SRC/ABL inhibitor. BFORE (Cortes JCO 2017): 12-mo MMR 47.2% vs 36.9%, 12-mo CCyR 77.2% vs 66.4% vs imatinib. AEs: diarrhea (~10.8% grade ≥3, early, subsides), transaminitis, myelosuppression; less cardiovascular signal than nilotinib. Approved for CP CML resistant/intolerant to prior therapy; usable in third or later lines (esp. for intolerance with a suitable mutation profile). Asciminib or ponatinib generally preferred for true resistance after multiple TKIs.
- Asciminib (Scemblix): mechanistically distinct STAMP (Specifically Targeting the ABL Myristoyl Pocket) inhibitor: allosteric, binds the vacant myristoyl pocket normally occupied by the myristoylated N-terminus of ABL1, NOT ATP-competitive; high selectivity for ABL1 with activity against ATP-site mutants including T315I. FDA Oct 2021 for CP CML after ≥2 prior TKIs (80 mg QD or 40 mg BID) and for T315I (200 mg BID). Oct 29, 2024 accelerated approval first-line for newly dx CP CML at 80 mg PO QD based on ASC4FIRST (Hochhaus NEJM 2024): week 48 MMR 68% asciminib vs 49% IS-TKIs (P=.001), vs imatinib 69% vs 40%. Favorable AE profile (grade ≥3 AEs 38% asciminib vs 44% imatinib vs 55% 2G-TKIs). Class AEs: thrombocytopenia, pancreatic enzyme elevation, hypertension, rare cardiovascular events. Consider for cardiovascular comorbidities.
Second-generation TKI vs imatinib (12-month efficacy)
Second-generation TKI vs imatinib12-month efficacy, %
| 2G TKI | CCyR vs imatinib (%) | MMR vs imatinib (%) | Transformation vs imatinib (%) |
|---|---|---|---|
| Nilotinib 300 mg BID | 80 vs 65 | 44 vs 22 | 1 vs 4 |
| Dasatinib 100 mg daily | 83 vs 72 | 46 vs 28 | 1.9 vs 3.5 |
| Bosutinib 400 mg daily | 77 vs 66 | 47 vs 37 | 1.6 vs 2.5 |
Later-line and T315I-active TKIs

- Ponatinib (Iclusig): third-gen, active against T315I. PACE (phase 2): among CP CML, MCyR 56% overall including 70% of T315I patients; AP CML major hematologic response 55%; BP CML major hematologic response 31%. Only TKI (besides asciminib 200 mg BID) effective against T315I. High rate of vascular events (MI, CVA, PAD); collaborate with cardiology to optimize risk factors. OPTIC (Cortes Blood 2021): response-adapted dosing, start 45 mg then reduce to 15 mg QD on achieving ≤1% IS, reduces arterial occlusive events while preserving efficacy; FDA label updated Dec 2020.
- Vodobatinib: third-gen TKI investigated for patients who progressed on 4 TKIs.
- Omacetaxine mepesuccinate (formerly homoharringtonine): a protein synthesis inhibitor that does NOT bind BCR-ABL; binds the A-site cleft of the large ribosomal subunit, blocking chain elongation. FDA-approved for CP or AP CML with resistance/intolerance to ≥2 TKIs; a historical treatment option at progression, not upfront (Synribo is commercially discontinued in the US).
Resistance & BCR-ABL1 kinase-domain mutations
BCR::ABL1 mutation-to-TKI guide (CRITICAL, must memorize)
BCR-ABL1 mutation-directed TKI selectionMust memorize
| Mutation / TKI | Selection |
|---|---|
| T315IGatekeeper | Ponatinib, asciminib (200 mg BID), omacetaxine, allogeneic transplant. Pan-resistant to imatinib, dasatinib, nilotinib, bosutinib. |
| Nilotinib | Use for V299L, T315A, F317L/V/I/C |
| Dasatinib | Use for Y253H, E255K/V, F359V/C/I |
| Bosutinib | Use for F317V/I/C, F359V/C/I, T315A, Y253H. E255K/V are poorly sensitive to bosutinib (limited data); prefer dasatinib, ponatinib, or asciminib. |
- Resistance patterns: bosutinib fails with T315I, V299L, G250E, or F317L (retains activity against F317V/I/C). Dasatinib fails with T315I/A, F317L/V/I/C, or V299L. Nilotinib fails with T315I, Y253H, E255K/V, or F359V/C/I.
- Asciminib resistance: myristoyl-pocket mutations (e.g. A337V, P465S); it maintains activity against most ATP-pocket mutations including T315I.
- Compound mutations (two mutations on the same allele) are particularly resistant.
Treatment-Free Remission (TFR) / discontinuation
- Overall success: about 50% of selected patients maintain response after stopping.
- Key trials: STIM (imatinib): ~41% maintained CMR after stopping; many who relapsed regained CMR on rechallenge. EURO-SKI: sustained MR4.0 for ≥3 years was the strongest predictor of successful discontinuation; molecular relapse-free survival ~61% at 6 months and ~50% at 24 months (so ~39% lost MMR by 6 months); most relapses occur within the first 6 months, but ~86% regain MMR and ~80% regain MR4 on restart; no progression to AP/BP. ENESTfreedom (frontline nilotinib): 51.6% in MMR or better at 48 weeks off therapy; 98.8% and 88.4% regained MMR and MR4.5 on reinitiation. ENESTop (imatinib then nilotinib): 57.9% in TFR at 48 weeks, 53.2% at 96 weeks; 92.9% regained MR4.0/MR4.5 on restart.
NCCN TKI discontinuation criteriaCriteria for TKI discontinuation (NCCN)
| Step | Criterion |
|---|---|
| Eligibility | Age ≥18 years. |
| Chronic phase CML, no history of AP or BP. | |
| On an approved TKI for at least 3 years. | |
| Stable molecular response (MR4, BCR-ABL1 ≤0.01% IS) for ≥2 years (5 years is even better), documented on ≥4 tests ≥3 months apart. | |
| Access to a reliable quantitative PCR with sensitivity ≥MR4.5 (≤0.0032% IS). | |
| Monitoring | Monthly for 6 months, then every 2 months through month 24 (ELN: through month 12), then every 12 weeks while in MMR. |
| Restart | Resume TKI within 4 weeks of loss of MMR (>0.1% IS), with monitoring every 4 weeks until MMR re-established, then every 3 months. |
- TKI withdrawal syndrome: musculoskeletal pain in ~25 to 40%, usually self-limited; NSAIDs.
- A high Sokal score at diagnosis is a concerning finding but TKI withdrawal can still be considered.
TKI toxicity comparison
- Class effects: all TKIs can cause myelosuppression, electrolyte disturbance, QT prolongation, and elevated LFTs.
TKI characteristic toxicities
| TKI | Characteristic toxicities |
|---|---|
| Imatinib | Fluid retention, periorbital edema, GI upset, rash, myalgias; hypophosphatemia and altered bone/mineral metabolism (bone-density effects variable, not a uniform decrease). Long-term follow-up: no significant late CV/pulmonary toxicity. |
| Dasatinib | Pleural effusions (~20%), pulmonary HTN (rare but serious), QTc, GI bleed / platelet dysfunction. |
| Nilotinib | PAD, hyperglycemia, hypercholesterolemia; Black box QT prolongation (hold if QTc >480); elevated LFTs, amylase/lipase (pancreatitis), bilirubin; low magnesium. Nilotinib is dosed BID; asciminib is also BID in some regimens (40 mg BID option, 200 mg BID for T315I). |
| Bosutinib | Diarrhea (prominent, early), transaminitis; less long-term experience. |
| Ponatinib | Black box arterial thrombosis (MI, CVA, PAD) and hepatotoxicity; VTE, pancreatitis, rash. |
| Asciminib | Thrombocytopenia, pancreatic enzyme elevation, hypertension, rare cardiovascular events (favorable overall profile). |
- TKI selection by comorbidity: pulmonary disease, CHF, or bleeding risk, avoid dasatinib; cardiovascular disease, diabetes, prolonged QTc, or pancreatitis, avoid nilotinib (and ponatinib for arterial disease). Older age favors imatinib.
- Sequencing: start imatinib/nilotinib/dasatinib/bosutinib, then, for intolerance or a favorable actionable mutation, switch to another second-generation TKI; for true resistance (esp. after multiple lines) prefer ponatinib or asciminib, guided by kinase-domain mutation testing and adherence assessment; for second relapse or T315I, use ponatinib (or asciminib); allo-HSCT beyond that. Bosutinib in third line mainly for intolerance with a sensitive mutation profile.
Advanced Phase Disease
- Accelerated phase: intensify TKI (2nd/3rd gen at higher dose, e.g. imatinib 600 mg, dasatinib 140 mg, nilotinib 400 mg BID, bosutinib 500 mg, ponatinib 45 mg); consider allo-HSCT if not in stable response.
- Blast phase, myeloid: TKI + AML-type induction (e.g. 7+3 + TKI), then allo-HSCT in second CP.
- Blast phase, lymphoid: TKI + ALL-type induction (hyper-CVAD or pediatric-inspired) +/- blinatumomab, then allo-HSCT.
- TKI for BP: dasatinib or ponatinib (better CNS penetration; ponatinib for T315I or multi-TKI failure).
- Goal: bridge to allo-HSCT, the only curative option for advanced CML.
Special Considerations
- CML in pregnancy: avoid TKIs in the first trimester (teratogenic). Options: interferon-alfa (safe), leukapheresis. Selected patients may resume imatinib or nilotinib after ~16 weeks under specialist care; avoid dasatinib throughout pregnancy (fetal hydrops); later-pregnancy safety not established for bosutinib, ponatinib, or asciminib. Plan pregnancy after sustained deep molecular response (CMR/MR4).
- Cardiovascular risk: nilotinib and ponatinib cause vascular events (PAOD, MI, CVA); screen ASCVD, control HTN, lipids, diabetes.
- Pleural effusion (dasatinib): dose interruption + diuretic +/- steroid; switch TKI for recurrent effusions.
- Pulmonary arterial hypertension (dasatinib): permanently discontinue dasatinib if PAH is confirmed (RHC/specialist evaluation); hemodynamics often improve after withdrawal but PAH persists in ~37%, sometimes needing PAH-directed therapy.
Veli Bakalov MD, Board Review Notes 2026
Practice guidelines
Official guidelines on each society's website (opens in a new tab). NCCN may ask for a free login.