Anal cancer
Anal cancer
Overview
- Epidemiology: ~11,000 new cases/yr in the US (ACS 2026 estimate 11,270), ~1,700 deaths; 5-yr relative survival ~70% (SEER). Female predominance (M:F roughly 2:3.5). Incidence is rising.
- HPV association: >90% of anal cancers are HPV-related (esp. HPV 16, 18). p16 is positive in most (approximately 90%) anal SCC, but a minority are HPV independent and p16 negative with worse prognosis.
- Histology: majority are squamous cell (epidermoid, keratinizing) or cloacogenic (basaloid, cuboidal, transitional, non-keratinizing) carcinoma. SCC is more common in the lower anus; cloacogenic in the high anus. Adenocarcinoma of the anal canal is treated as rectal cancer. Neuroendocrine carcinoma and melanoma also occur.
- Risk factors (#1 is HPV): female sex (~2×, esp. >45 with HPV 16), history of high-grade cervical/vulvar/vaginal dysplasia or cervical cancer (RR ~4.6 in SEER), MSM, number of lifetime partners (RR ~4.5 in women with >10 partners), genital warts, smoking (RR ~1.9 at 20 pack-yr, ~5.2 at 50 pack-yr), receptive anal intercourse, chronic immunosuppression (solid-organ transplant, associated with ↑ HGSIL and carcinoma), and HIV (~40×). Anal cancer rates have NOT declined in the HAART era (unlike Kaposi sarcoma and NHL).
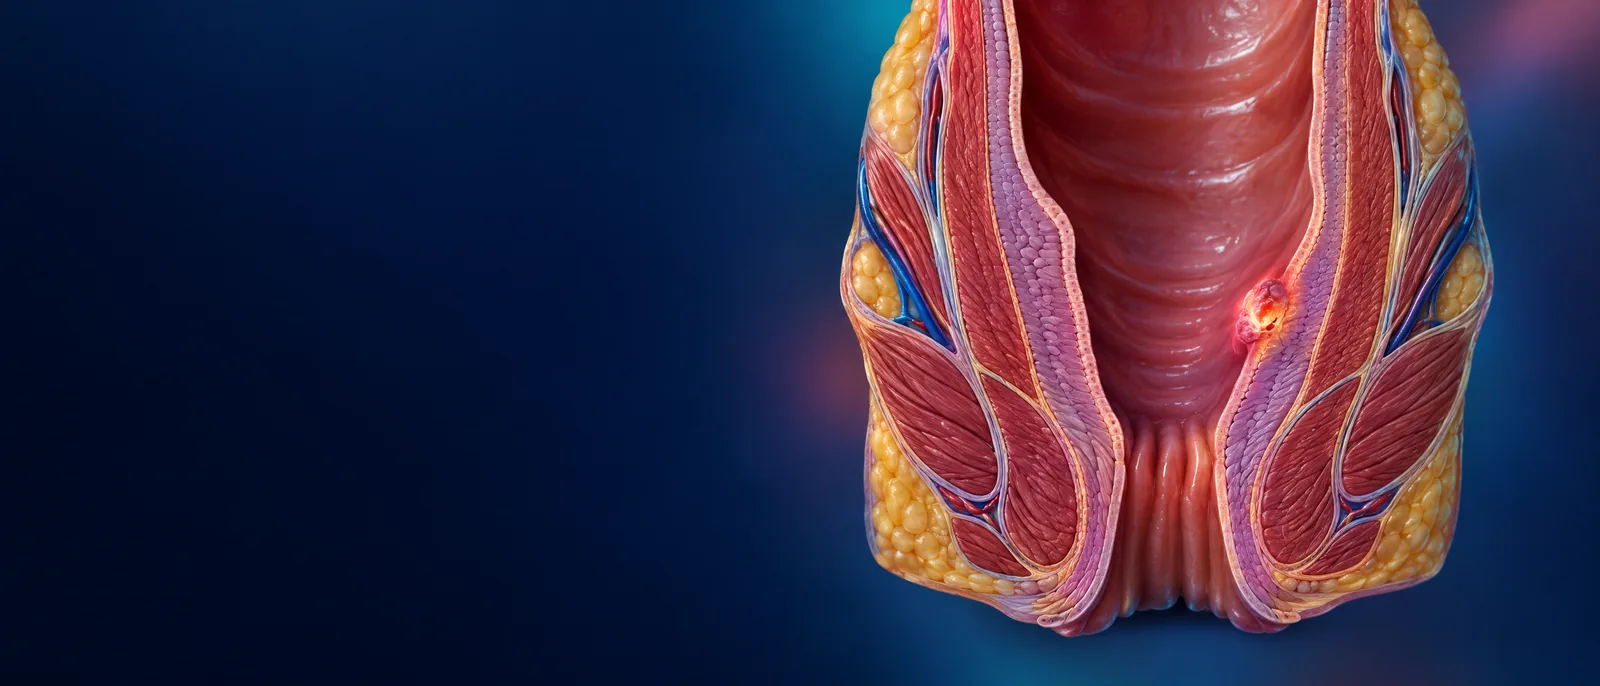
Anatomy / lymphatic drainage

- Above dentate line: drains to mesorectal and internal iliac nodes (like low rectal cancer) → N1a.
- Below dentate line: drains to superficial inguinal nodes (N1a) and external iliac nodes (N1b; external iliac plus any N1a = N1c).
- All of these are N1 nodes per AJCC 8th edition (nodal location does not further change the stage).
Workup & staging
- Workup: anorectal and inguinal node exam (palpation, FNA if abnormal), anoscopy, biopsy; CT chest, CT or MRI abdomen/pelvis, PET/CT, and gynecologic exam including cervical cancer screening.
- PET/CT: a meta-analysis showed PET/CT changed nodal staging (vs CT alone) in ~28% of patients. PET/CT may be considered (not mandatory) for perianal skin SCC, particularly with suspected nodal or more extensive disease. (Note: pelvic MRI is recommended for locoregional T/N staging and RT planning; EUS has only a limited role in anal cancer.)
- HIV testing is mandatory in all newly diagnosed anal SCC.
- Tumor markers: no role for CEA or other markers in localized disease (though 20 to 39% have elevated CEA).
- Staging (AJCC): T by size (T1 ≤2 cm, T2 >2 to 5 cm, T3 >5 cm, T4 invades adjacent organs) plus lymph node status.
- Screening: anal Pap + high-resolution anoscopy (HRA) for high-risk groups (HIV+, MSM, prior HPV-related cancer, transplant recipients). ANCHOR study showed treating high-grade AIN reduces progression to anal SCC.
Treatment of localized disease (Nigro chemoRT)

- Definitive chemoRT is SOC: excellent cure rates and 70 to 85% sphincter preservation. APR is NOT initial therapy; it is reserved for salvage.
- Nigro protocol (Nigro ND, Cancer 1983, PMID 6831348; Wayne State, 28 pts): concurrent 5-FU (1000 mg/m²/day on days 1 to 4 and 29 to 32) + mitomycin C (single 15 mg/m² bolus on day 1) with RT (originally 30 Gy in 15 fractions to pelvis, medial inguinal nodes, and anal canal). APR was originally planned for all, but 5/6 initial APR specimens had no residual tumor, so APR became salvage only. cCR ~86% with chemoRT alone at week 11.
- 5-FU + mitomycin > 5-FU + cisplatin (RTOG 98-11; ACT-II showed cisplatin was not better than mitomycin (cCR 90.5% vs 89.6%) and maintenance chemo added no benefit, so 5-FU/mitomycin remained standard). Mitomycin remains preferred; numerous later trials failed to improve on Nigro.
- Alternative regimens: capecitabine + mitomycin + RT, or 5-FU + cisplatin + RT.
- IMRT preferred (RTOG 0529): reduces skin and GI toxicity vs 3D-CRT. Typical RT dose 45 to 59 Gy.
- Mitomycin C AEs: severe/prolonged myelosuppression, pulmonary fibrosis, hemolytic-uremic syndrome, therapy-related MDS.
- Upfront local excision: only for very favorable superficial tumors, i.e. superficially invasive SCC (SISCCA): completely excised, invasion ≤3 mm below the basement membrane, horizontal spread ≤7 mm (no gross size cutoff).
- HIV+ patients: if CD4 >200, use standard chemoRT doses; consider dose adjustment if symptomatic HIV or CD4 <200. Do NOT withhold therapy because of HIV; initiate/continue ART.
- Prognosis: male sex, node-positive, skin ulceration, and tumor >5 cm are associated with worse PFS and OS.
Response assessment and follow-up
- Anal SCC regresses slowly, can take up to ~26 weeks (~6 months). ACT-II lesson: of patients not in cCR at 11 weeks, 72% (151 of 209, among patients attending all three assessments) achieved cCR by 26 weeks (whole-trial cCR rates 52% at 11 wk, 71% at 18 wk, 78% at 26 wk); 26 weeks became the validated assessment time point (vs 11 weeks in the original Nigro protocol).
- After completion of chemoRT: DRE and inguinal exam at 8 to 12 weeks (no MRI).
- After cCR: DRE, inguinal node exam, and anoscopy q3 to 6 mo for 5 yr, with CT TAP or MRI annually for 3 yr in T3-T4 or node-positive disease.
- No cCR but no progression: serial reassessment (regression can continue up to ~6 mo after chemoRT), with biopsy confirmation. Salvage APR only for biopsy-proven progression or persistence after an adequate observation interval. (+ groin dissection if inguinal nodes positive).
Treatment of metastatic disease
- Rate of metastasis after definitive CRT: ~10% (UKCCCR), ~17% (EORTC), ~22% (ACT-II).
- 1L: carboplatin + paclitaxel is the SOC chemo backbone; ↑ OS vs 5-FU/cisplatin in InterAACT (and better tolerated). Other regimens: 5-FU + cisplatin, FOLFCIS, mFOLFOX6, modified DCF (mDCF; Epitopes-HPV02).
- After starting 1L chemo, reevaluate and consider chemoRT to the primary (5-FU/capecitabine) for local control.
- Chemo + PD-1 (1L): POD1UM-303 (Rao ESMO 2024 / Lancet 2025): retifanlimab + carboplatin/paclitaxel vs placebo + carbo/paclitaxel in advanced/metastatic anal-canal SCC met the primary PFS endpoint (HR ~0.63): the first positive phase 3 IO + chemo in this disease. FDA approved retifanlimab + carboplatin/paclitaxel in 2025 as 1L therapy for inoperable locally recurrent or metastatic squamous anal-canal cancer, displacing carbo/paclitaxel alone (InterAACT) as SOC 1L. (ECOG-ACRIN EA2176 tested carbo/paclitaxel ± nivolumab.)
- 2L+ single-agent PD-1 (for checkpoint-naive patients; efficacy data are from IO-naive populations, not established after prior first-line PD-1):
- Retifanlimab (Zynyz): POD1UM-202 (Spano JITC 2024, single-arm phase 2, pretreated): ORR 14%, mDOR 9.5 mo. FDA approved May 15, 2025 (with the 1L combination) as a single agent for locally recurrent/metastatic SCAC progressing on or intolerant to platinum chemo (first approved Mar 2023 for Merkel cell carcinoma).
- Nivolumab (NCI 9673): ORR ~24%, mPFS ~4.1 mo, mOS ~11.5 mo.
- Pembrolizumab (KEYNOTE-028/158): ORR ~12 to 17%; used off-label.
Related: appendiceal mucinous / goblet cell adenocarcinoma
- Appendiceal mucinous cancer and goblet cell adenocarcinoma (formerly goblet cell carcinoid) have their own terminology and WHO grading. Localized invasive appendiceal adenocarcinoma and goblet cell adenocarcinoma: oncologic resection, usually right hemicolectomy with regional nodal evaluation. Complete cytoreductive surgery + HIPEC is reserved for peritoneal dissemination (not universally accepted). Systemic therapy follows colon-cancer (not neuroendocrine) criteria for high-grade/poorly differentiated tumors. Refer to expert pathology review and specialized multidisciplinary teams.
High-yield anal pearls
- HPV-driven (esp. 16, 18); >90% HPV-related, p16+. Screen high-risk populations (ANCHOR: treating high-grade AIN reduces progression).
- Nigro regimen: 5-FU + mitomycin C + RT (IMRT preferred). APR is salvage only.
- Assess response at 26 weeks, not 11 (first exam at 8 to 12 wk, but do not call failure or salvage before 26 wk; slow regression; ACT-II).
- HIV testing mandatory; still treat HIV+ with standard chemoRT (with ART).
- 1L metastatic: carbo + paclitaxel (InterAACT), now retifanlimab + carbo/paclitaxel (POD1UM-303, FDA 2025).
- Retifanlimab (FDA May 2025): 1L with carboplatin/paclitaxel for inoperable locally recurrent or metastatic anal SCC (POD1UM-303) and single agent after platinum (POD1UM-202); nivolumab/pembrolizumab also active.
- Anal melanoma: separate mucosal-melanoma entity (surgery + IO).
Veli Bakalov MD, Board Review Notes 2026
Practice guidelines
Official guidelines on each society's website (opens in a new tab). NCCN may ask for a free login.