Salivary gland tumors
Salivary gland tumors
Overview

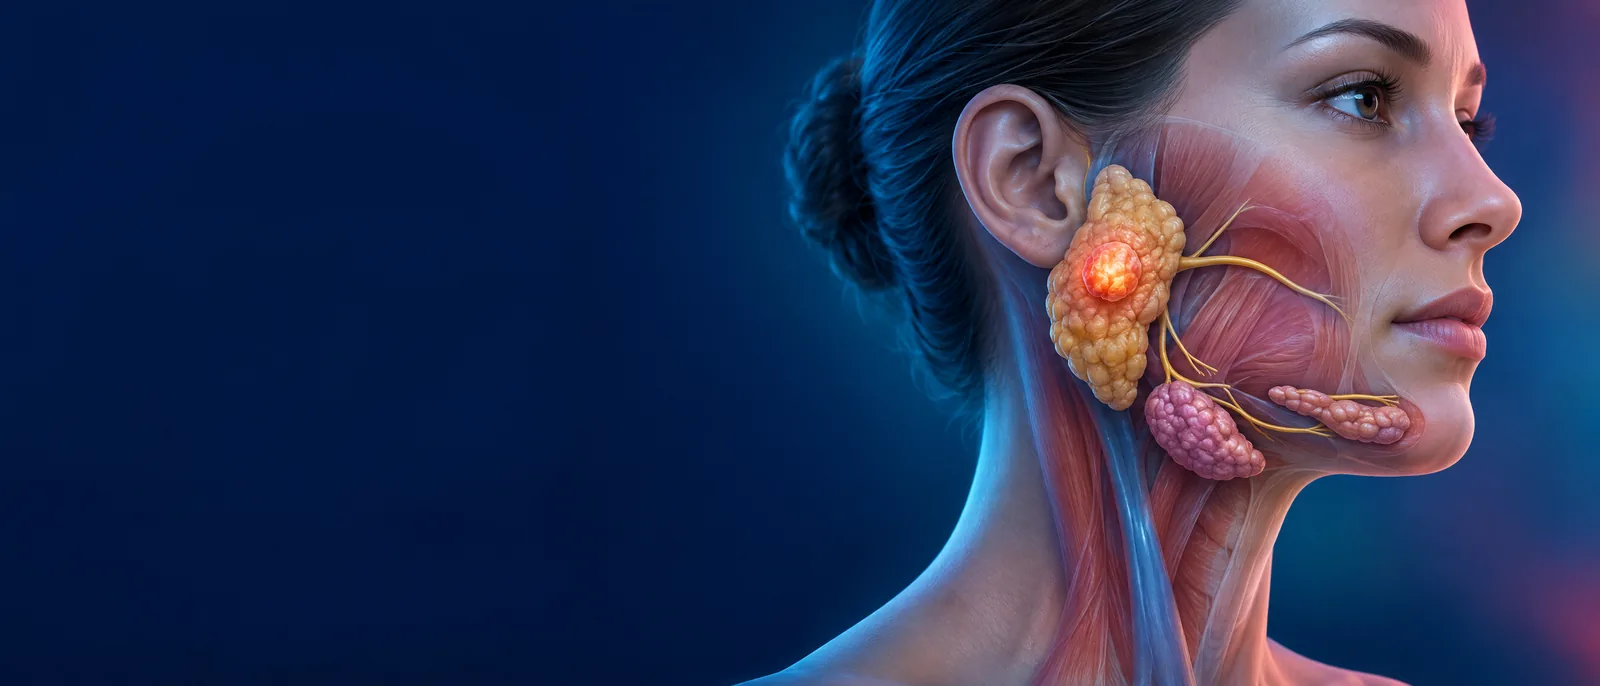
- Epidemiology: cancers of the major (parotid, submandibular, sublingual) and minor salivary glands are uncommon, <10% of epithelial head and neck tumors. The WHO classification (5th ed, 2022) lists 21 malignant epithelial salivary tumor entities; their small numbers and heterogeneity make them hard to study.
- Risk factors: tobacco and alcohol are NOT risk factors (unlike HNSCC); there may be an association with prior radiation exposure.
- Rule of thumb: "the smaller the gland, the higher the chance of malignancy," parotid ~75% benign, submandibular ~50%, sublingual/minor mostly malignant.
- Cell of origin: adenoid cystic carcinoma and adenocarcinoma arise from intercalated ducts; mucoepidermoid carcinoma from the secretory (excretory) ducts.
Histologic types
- Pleomorphic adenoma: most common salivary tumor (benign); mixed epithelial/myoepithelial with variable architecture. Diagnosed by FNA; resect because of risk of transformation (carcinoma ex pleomorphic adenoma).
- Warthin tumor: second most common benign; bilateral in ~10%; smokers; lymphoid stroma.
- Mucoepidermoid carcinoma (MEC): most common malignant. CRTC1-MAML2 fusion (low/intermediate grade, favorable). Grade drives prognosis; high-grade MEC behaves aggressively. HER2+ in some (trastuzumab + chemo active).
- Adenoid cystic carcinoma (ACC): MYB-NFIB fusion; most common in minor glands. Perineural (neurotropic) spread is the HALLMARK; highest propensity of any subtype for distant metastasis (lung), yet often indolent and ultimately fatal.
- Salivary duct carcinoma: aggressive adenocarcinoma with rapid metastasis; microscopically resembles ductal breast cancer; frequently androgen receptor (AR)+ and HER2+.
- Secretory carcinoma (formerly MASC, mammary analog secretory carcinoma): ETV6-NTRK3 fusion; often mistaken for acinic cell carcinoma.
- Other: acinic cell, polymorphous adenocarcinoma. High-grade MEC or adenocarcinoma correlates with aggressive behavior and eventual metastasis; low-grade histologies are more often cured by local therapy alone.
Workup & staging
- FNA (or core needle) first for major-gland masses, avoiding open biopsy; accessible minor salivary-gland/submucosal lesions may undergo incisional biopsy.
- Imaging: MRI of primary (better soft-tissue definition than CT); CT for bone; PET if advanced.
- Facial nerve (CN VII) assessment for parotid tumors.
- AJCC staging by site, size, extension, LN status, and metastasis.
Treatment: localized / locally advanced
- Surgery is the mainstay for all primary and recurrent resectable disease (including pleomorphic adenoma, given transformation risk).
- Parotid: superficial parotidectomy (most), total parotidectomy for deep-lobe involvement; preserve the facial nerve when possible.
- Submandibular/sublingual: complete gland excision ± selective neck dissection.
- Neck dissection: elective for selected cN0 high-grade or T3 to T4 tumors; therapeutic for clinically node-positive disease.
- Adjuvant RT for adverse pathology: high grade, T3 to T4, close/positive margins, perineural invasion (esp. ACC), LN+, ECE.
- By analogy to HNSCC, concurrent cisplatin is sometimes offered for adverse features (positive margins, ECE), but ASCO 2021 recommends against routine concurrent chemoRT outside a trial (no randomized benefit; RTOG 1008).
- For unresectable tumors, definitive radiation-based therapy is used. Neutron beam therapy has shown promise for ACC, but toxicity is a concern and the RTOG-MRC neutron vs photon trial had significant methodological limitations; proton therapy at experienced centers is an alternative.
Systemic therapy (recurrent / metastatic)

- General approach: many salivary carcinomas (especially ACC) are indolent; defer systemic therapy until substantial growth is documented on serial imaging within ~6 months or symptoms are imminent (e.g., bronchial obstruction).
- Salivary duct carcinoma (treat like breast/prostate):
- AR+: androgen deprivation therapy (e.g., bicalutamide + LHRH agonist).
- HER2+: trastuzumab + chemo (taxane); T-DM1 and T-DXd active.
- HER2 IHC 3+ (tumor-agnostic T-DXd): DESTINY-PanTumor02 (Meric-Bernstam JCO 2024, PMID 37870536), pan-tumor phase 2 (salivary tumors within the other-tumors cohort); ORR 37.1% overall in HER2-expressing tumors, 61.3% in central IHC 3+. Basis for the FDA tumor-agnostic accelerated approval Apr 5, 2024 of T-DXd for unresectable/metastatic HER2 (IHC 3+) solid tumors after prior systemic therapy and with no satisfactory alternative treatment options, now an on-label option for HER2 IHC 3+ salivary duct carcinoma.
- Adenoid cystic carcinoma (ACC): observe if asymptomatic/indolent. Antiangiogenic TKIs are preferred systemic options with modest activity in progressive ACC, but have not been shown superior to cytotoxic chemo in head-to-head trials: lenvatinib (two phase 2 trials: ORR ~12 to 16%, mPFS ~9 to 17.5 mo), axitinib also active. Cytotoxic options (symptomatic disease): cyclophosphamide + doxorubicin + cisplatin or single agents. Pembrolizumab if MSI-high.
- Secretory carcinoma / NTRK fusion: larotrectinib (ORR ~75%, CR ~22%, salivary gland the most common tumor treated) or entrectinib (ORR ~57%, CR ~7%, mDOR ~10 mo). Reasonable to test all salivary tumors for NTRK fusions, especially when histology is unclear.
- RET fusion: selpercatinib (tumor-agnostic).
- Dual checkpoint blockade: ipilimumab + nivolumab has preliminary activity in non-ACC salivary gland cancers. Single-agent pembrolizumab has modest activity under the tumor-agnostic MSI-H/dMMR or TMB-high indications; PD-L1 CPS ≥1 alone is not an established indication.
- Chemo (last resort): carboplatin + paclitaxel, or CAP.
High-yield pearls
- Parotid = mostly benign; minor glands = mostly malignant. Tobacco/alcohol are not risk factors for salivary carcinoma (smoking is linked to benign Warthin tumor).
- ACC: MYB-NFIB, perineural invasion, late lung mets, indolent course; follow with serial imaging.
- MEC: CRTC1-MAML2; grade-driven prognosis.
- Salivary duct carcinoma = AR+/HER2+; treat like breast/prostate (anti-AR, HER2 agents, T-DXd if IHC 3+).
- Secretory carcinoma (MASC): ETV6-NTRK3; larotrectinib or entrectinib is treatment of choice for metastatic disease or when surgery would cause severe morbidity.
- Avoid open biopsy; use FNA. Surgery is the mainstay, RT for high-risk features; pleomorphic adenoma must be resected (transformation risk).
Veli Bakalov MD, Board Review Notes 2026
Practice guidelines
Official guidelines on each society's website (opens in a new tab). NCCN may ask for a free login.