Gastrointestinal stromal tumor (GIST)
GIST Gastrointestinal Stromal Tumor
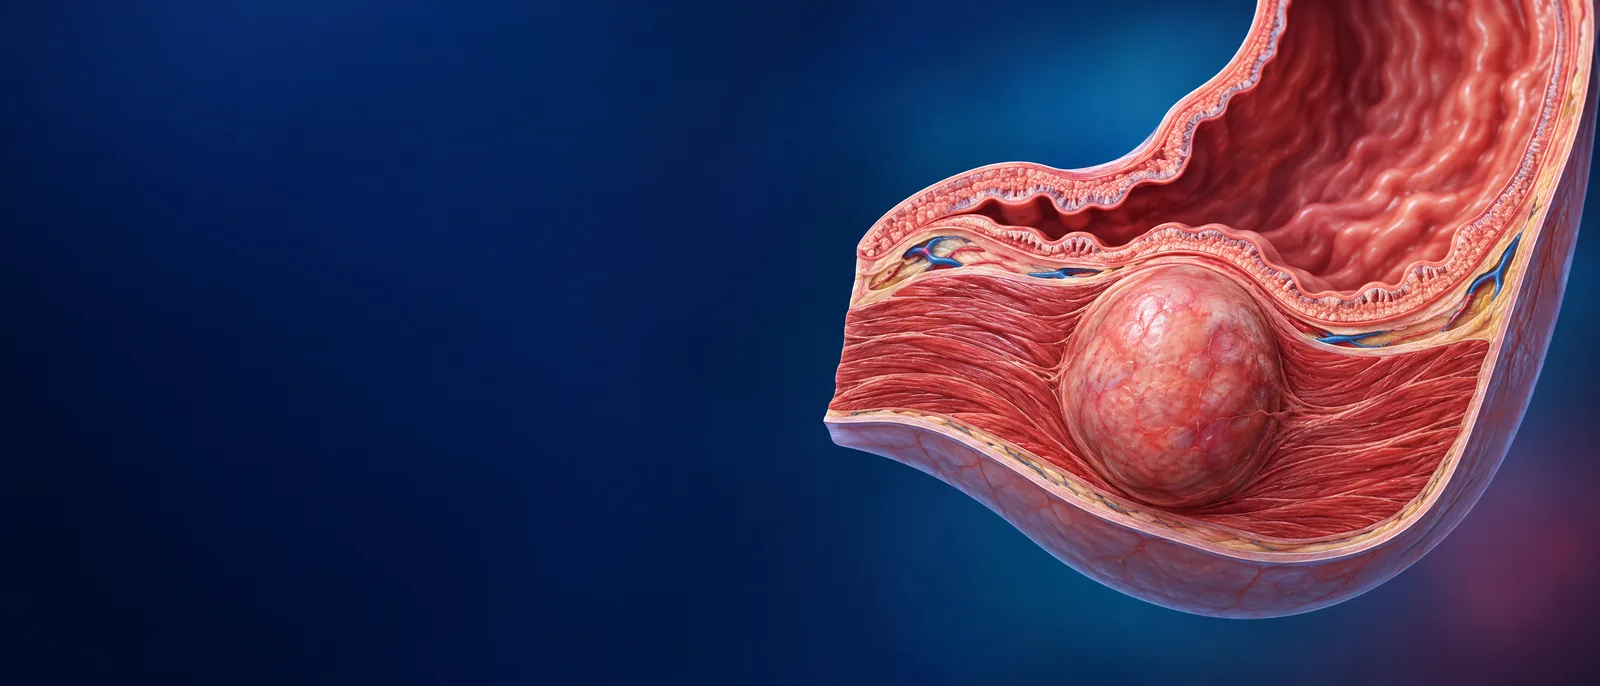
Overview
- Origin: malignant counterpart of the interstitial cells of Cajal (the GI pacemaker cells). Most common mesenchymal/soft-tissue tumor of the GI tract.
- Incidence: ~5,000 to 6,000/yr US.
- Sites: stomach ~60%, small bowel ~30%, colorectum ~5%, esophagus <1%, remainder extraintestinal/abdominal.
- Metastatic pattern: liver, abdomen, peritoneum. Almost completely resistant to cytotoxic chemotherapy.
- IHC: CD117 (KIT) and/or DOG1 (discovered on GIST), CD34. Vimentin+; desmin and S100 generally negative.
Molecular drivers (drive therapy)

- ~90% harbor mutually exclusive KIT or PDGFRA mutations.
- KIT exon 11 (~70%): prognosis heterogeneous (557/558 deletions carry higher localized recurrence risk), best imatinib sensitivity (imatinib 400 mg/d), mOS ~66 mo.
- KIT exon 9 (~10%): worse prognosis, needs imatinib 800 mg/d, mOS ~38 mo.
- KIT wild-type: mOS ~40 mo.
- PDGFRA exon 18 D842V: imatinib-RESISTANT. Localized D842V often indolent (favorable natural history); avapritinib markedly improves advanced-disease outcomes but is not adjuvant and does not reclassify primary-tumor recurrence risk.
- PDGFRA exon 12: behaves like KIT exon 11 and responds to TKIs.
- Wild-type (KIT/PDGFRA WT, ~10 to 15%): SDH mutation/deficiency (SDH-A, SDH-B, SDH-C, or SDH-D, or SDHC promoter methylation in Carney triad, ~10%), BRAF or NF1 mutations, NTRK fusions (<2%). SDH-deficient GIST is typically young/pediatric, gastric, and imatinib-resistant (Carney triad, Carney-Stratakis).
Mutation-directed TKI targeting
GIST: mutation-directed TKI targeting
| Drug | Mutations targeted |
|---|---|
| Imatinib | KIT exon 9 (use 800 mg) and KIT exon 11 (use 400 mg) |
| Sunitinib | Secondary resistance mutations in exon 13 (V654A) and exon 14 (T670I), which account for ~60% of imatinib resistance |
| Regorafenib | KIT exon 17 activation-loop mutations (D816E, D820A/Y, N822K) |
| Ripretinib | Pan-KIT and PDGFRA kinase switch-control inhibitor (broad activity vs resistance mutations) |
| Avapritinib | PDGFRA exon 18 (D842V), KIT exon 17 |
- Sequence mnemonic: Imatinib → Sunitinib → Regorafenib → Ripretinib ("I'm at Sunny Resort River").
Risk stratification (Miettinen / NIH)
- Key factors: tumor size, mitotic count (per 5 mm² or 50 HPF), primary site (small bowel worse than gastric), and tumor rupture. Risk assignment guides adjuvant therapy.
- Mitotic count cannot be relied upon if the patient received preoperative imatinib.
- Surgery is the only potentially curative therapy, but recurrence is common in higher-risk GIST. Complete resection is possible in ~85% of patients; ~50% of these develop recurrence or metastases (median time to recurrence ~2 yrs), with 5-yr OS dependent on recurrence risk and adjuvant therapy (even high-risk SSG XVIII ~86 to 92% at 5 yr).
Localized GIST
- Surgery with negative margins is the cornerstone. Avoid routine lymphadenectomy (LN spread rare); remove clinically involved nodes; SDH-deficient GIST is an exception (nodal spread more common).
- Neoadjuvant imatinib to downstage (especially rectal and large gastric tumors). RTOG 0132/ACRIN 6665 (Eisenberg BL, J Surg Oncol 2009): preoperative imatinib 600 mg daily for 8 to 12 weeks gave PR 7% and SD 83% in the localized group (5% and 91% in the metastatic group); 5-yr PFS 57% localized vs 30% metastatic.
- Criticism: preoperative duration was very short. Radiographic partial responses can occur within 8 to 12 weeks, and maximal radiographic response generally occurs after 3 to 9 months of treatment.
- Adjuvant imatinib 400 mg/d for high-risk localized GIST.
- Duration 3 yrs superior to 1 yr (SSG XVIII/AIO). 5-yr RFS 65.6% vs 47.9% (initial analysis); 10-yr RFS 53% vs 42% (HR 0.66; P = .003); 5-yr OS 92% vs 86%; 10-yr OS 79% vs 65% (HR 0.55; P = .004).
- 6 yrs may be considered (NCCN listing) for very high risk.
- Skip adjuvant imatinib for PDGFRA D842V (imatinib-resistant); also avoid in NF1-associated and SDH-deficient GIST.
Advanced / metastatic GIST

- 1L imatinib 400 mg/d (mOS ~5 yrs). MetaGIST (JCO 2010) meta-analysis of SWOG 0033/CALGB 150105 and EORTC 62005: imatinib 800 mg for exon 9 improves PFS but not OS; imatinib 400 mg for exon 11.
- Avapritinib (Ayvakit) 1L for PDGFRA D842V. NAVIGATOR (Heinrich MC, Lancet Oncol 2020, PMID 32615108): ORR 88% (9% CR, 79% PR) in 56 D842V patients; FDA label analysis of 43 exon 18 mutants (38 with D842V): ORR 84% (7% CR, 77% PR), D842V ORR 89% (8% CR, 82% PR); mDOR ~27 mo. FDA Jan 9, 2020 for unresectable/metastatic PDGFRA exon 18 (including D842V) GIST.
- 2L (post-imatinib): sunitinib. Demetri GD, Lancet 2006 (imatinib-resistant GIST): mTTP 27.3 wk vs 6.4 wk (HR 0.33, P < .0001); mOS not reached (HR 0.49, P = .007). AEs: fatigue, diarrhea, skin discoloration, nausea, HTN, hypothyroidism.
- 3L: regorafenib. Demetri GD, Lancet 2013 (GRID; prior imatinib and sunitinib): mPFS 4.8 vs 0.9 mo (HR 0.27, P < .0001); mOS not significant (HR 0.77, P = .199, crossover confounded). AEs: HTN, hand-foot skin reaction.
- 4L: ripretinib (Qinlock). INVICTUS (Blay, Lancet Oncol 2020; prior imatinib, sunitinib, regorafenib): mPFS 6.3 vs 1.0 mo (HR 0.15); mOS 15.1 vs 6.6 mo. FDA May 15, 2020 for ≥4L GIST. Switch-control inhibitor active vs many imatinib-resistance mutations.
- Additional later-line options: sorafenib, nilotinib, dasatinib (for PDGFRA D842V), pazopanib; everolimus + TKI; avapritinib in later lines for non-D842V (modest activity).
- Bezuclastinib (CGT9486): selective KIT exon 17/18 inhibitor; PEAK phase 3 (bezuclastinib + sunitinib vs sunitinib, 2L post-imatinib GIST) was positive: mPFS 16.5 vs 9.2 mo (HR 0.50), ORR 45.6% vs 25.8%, with more grade ≥3 toxicity. NDA under FDA priority review (PDUFA Nov 30, 2026); still investigational for GIST as of Sep 2026. SUMMIT is in nonadvanced systemic mastocytosis.
- Pimitespib (Jeselhy), HSP90 inhibitor: CHAPTER-GIST-301 (Kurokawa, Ann Oncol 2022, PMID 35803734) in 4L+ GIST after imatinib/sunitinib/regorafenib: mPFS 2.8 vs 1.4 mo placebo (HR 0.51). Japan approval Jun 2022 (not FDA-approved). Notable AE: night blindness (transient ocular toxicity).
- INTRIGUE ctDNA exploratory analysis (Heinrich, Nat Med 2024): in 2L GIST with ctDNA-detected KIT exon 11 plus secondary exon 17/18 mutations, ripretinib had superior mPFS vs sunitinib (14.2 vs 1.5 mo), supporting NGS/ctDNA-guided TKI selection; ripretinib favored only in the KIT exon 11 + exon 17/18-only subgroup (not with co-occurring exon 13/14, which favored sunitinib, nor exon 9). In 2L KIT exon 11 GIST overall, sunitinib remains preferred (INTRIGUE was negative for ripretinib superiority).
High-yield GIST pearls
- KIT (CD117)+ is the hallmark; DOG1+ is also reliable.
- Imatinib 1L for KIT exon 11; 800 mg/d for exon 9.
- PDGFRA D842V = imatinib-resistant → avapritinib.
- SDH-deficient GIST (young, gastric, KIT/PDGFRA WT): imatinib-resistant; consider sunitinib, regorafenib, temozolomide, or clinical trial.
- Adjuvant imatinib × 3 yrs for high-risk resected GIST.
- Sequence: imatinib → sunitinib → regorafenib → ripretinib.
Veli Bakalov MD, Board Review Notes 2026
Practice guidelines
Official guidelines on each society's website (opens in a new tab). NCCN may ask for a free login.